The featured image and supporting patient illustrations are AI-generated and do not depict actual patients.
ASPC Patient Education · Updated 26 October 2026
At a glance
Pain over the deltoid region is not enough to diagnose deltoid tendinitis. Rotator cuff problems, bursitis, neck pain and injury can feel similar. Treatment should follow an assessment of the actual source of pain.
General patient information. Diagnosis and treatment should be individualized by a qualified healthcare professional.
Get help promptly: New inability to lift the arm after injury or chest symptoms needs urgent review.
In this guide
- What Is Deltoid Tendinitis?
- Causes and Risk Factors
- Symptoms and Pain Location
- Does it cause muscle weakness?
- Stages and Recovery Time
- Stage 1: Irritable or painful phase
- Stage 2: Load rebuilding phase
- Stage 3: Return-to-function phase
- Clinical assessment and rehabilitation
- What the assessment includes
- Clinical assessment and rehabilitation
- Nutrition and Daily Tips
- Other Conditions and When to Get Help
- Final Takeaway
- Common questions
- Sources and further reading
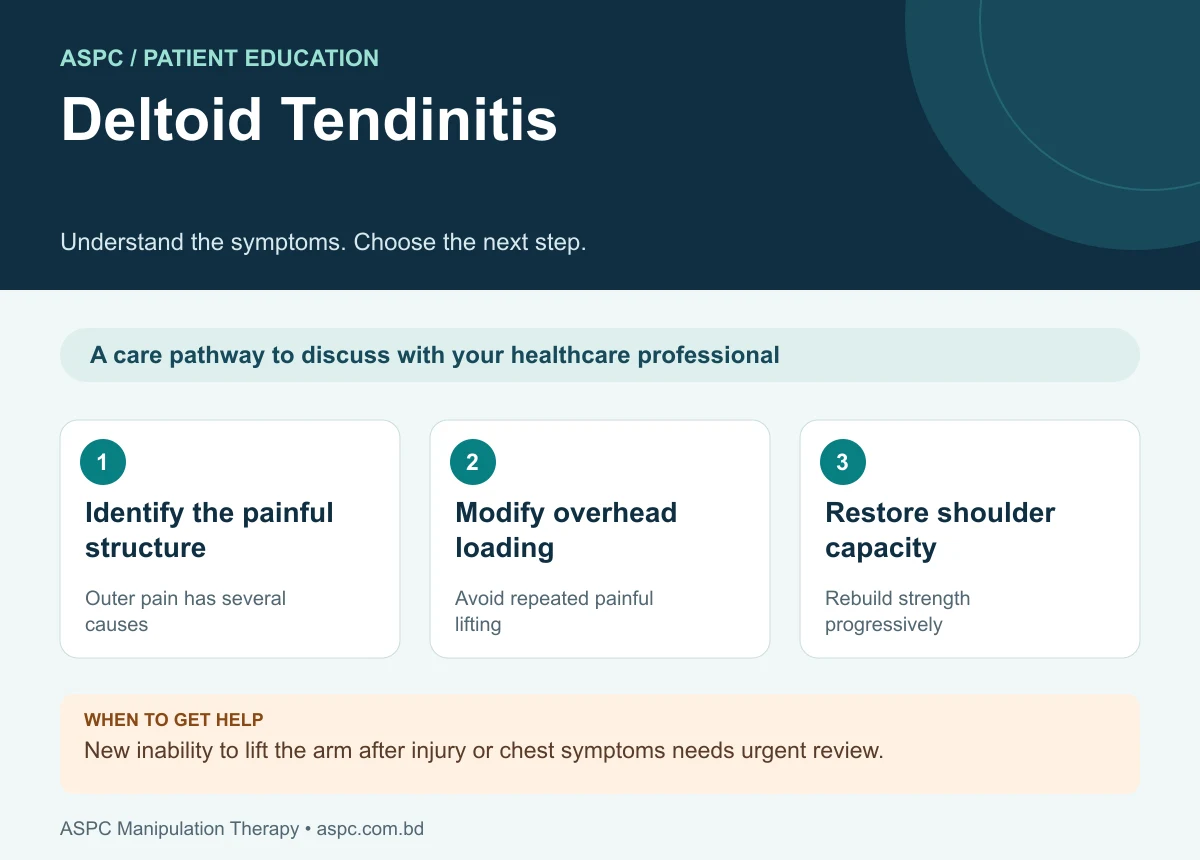
- Identify the painful structure: Outer pain has several causes.
- Modify overhead loading: Avoid repeated painful lifting.
- Restore shoulder capacity: Rebuild strength progressively.
Deltoid tendinitis, often described more broadly as deltoid tendinopathy, refers to pain and irritation involving the deltoid muscle’s tendon or its attachment around the shoulder. It may cause pain when lifting the arm, reaching overhead, carrying objects or performing repeated shoulder movements. Because pain in this region can also arise from rotator cuff disease, bursitis, acromioclavicular joint problems or referred neck pain, an accurate clinical assessment is important.
Symptoms may develop after a sudden increase in activity, repeated loading or a direct injury, although a precise cause is not always identified. Management usually focuses on identifying the painful structure, temporarily modifying aggravating loads and gradually restoring shoulder strength and function. Evidence specific to isolated deltoid tendinitis is limited; therefore, rehabilitation principles for shoulder tendinopathy should be applied cautiously and individualized to the clinical findings.
What Is Deltoid Tendinitis?
The deltoid is the large, triangular muscle covering the shoulder. It arises from the lateral third of the clavicle, the acromion and the spine of the scapula, and inserts on the deltoid tuberosity of the humerus. Its anterior, middle and posterior portions contribute to shoulder flexion, abduction and extension, respectively, while working with other muscles to move and control the arm. The term “deltoid tendinitis” is commonly used for painful irritation around the deltoid’s tendon or attachment, but clinicians may use “tendinopathy” when the problem reflects load-related tendon pain without clear evidence of acute inflammation.
Pain felt over the outer shoulder does not automatically mean that the deltoid tendon is the source. The rotator cuff, subacromial bursa, acromioclavicular joint and cervical spine can produce similar symptoms. Isolated deltoid insertional tendinopathy is not as well studied as rotator cuff tendinopathy, so diagnosis depends on the history, examination and exclusion of more likely causes rather than on the symptom location alone.
Causes and Risk Factors
Deltoid-region pain may follow repeated or unfamiliar loading, a rapid increase in training volume, direct trauma or work that requires frequent lifting. However, the same symptoms can arise from neighbouring shoulder structures. The diagnosis should therefore be based on a combination of symptom behaviour, examination findings and, when indicated, further investigation rather than on one presumed cause.
- Repeated or increased loading: sudden increases in overhead exercise, throwing, lifting or repetitive work may exceed the shoulder’s current load tolerance. A temporal relationship supports the possibility of a load-related disorder but does not confirm that the deltoid tendon is responsible.
- Direct trauma or muscle injury: a blow, fall or forceful contraction may injure the deltoid muscle or its attachment. Marked bruising, swelling, sudden weakness or loss of active movement requires assessment for a more substantial injury.
- Insufficient recovery: repeatedly performing painful shoulder activity without adequate recovery may maintain symptoms. Relative rest means reducing provocative loads, not automatically immobilizing the shoulder for a prolonged period.
- Coexisting shoulder disorders: rotator cuff tendinopathy, subacromial pain, acromioclavicular joint disorders and glenohumeral conditions can mimic deltoid-region pain. These should be considered during differential diagnosis.
- Postural, occupational and sporting demands: repetitive reaching, carrying loads away from the body and overhead sport can increase shoulder demand. These activities are potential load contributors, not proof of a specific tendon lesion.
- Age and general health: tendon symptoms can occur across adulthood. Evidence does not support a specific age or sex pattern for isolated deltoid tendinitis; clinicians should consider the person’s health, training history and functional demands.
Not everyone exposed to these factors develops symptoms, and pain around the deltoid may have a different cause. Persistent symptoms, significant weakness, traumatic onset or progressive loss of function warrant professional assessment to clarify the diagnosis.
Symptoms and Pain Location
The main symptom is pain around the outer or lateral shoulder, particularly during activities that load or raise the arm. Symptoms alone cannot reliably identify the affected structure, so consider clinical assessment if you notice the following:
- Pain over the lateral shoulder or near the deltoid attachment
- Pain when lifting the arm, reaching overhead or carrying an object
- Discomfort during repeated shoulder exercise, throwing or lifting
- Tenderness around the painful area, sometimes with pain after activity
- Difficulty with dressing, grooming, work tasks or sport because of shoulder pain
Pain may be felt over the deltoid region and upper arm. Pain that travels below the elbow, is associated with tingling or numbness, or changes substantially with neck movement may indicate cervical or nerve involvement rather than an isolated deltoid tendon problem.
Urgent warning: Seek emergency medical care for shoulder or arm pain accompanied by chest pressure, shortness of breath, sweating, faintness or pain spreading to the jaw. Urgent assessment is also needed after major trauma, with visible deformity, a hot swollen joint with fever, or sudden profound weakness.
Does it cause muscle weakness?
Pain can temporarily inhibit muscle performance, and reduced activity may lead to deconditioning. However, obvious loss of strength, a sudden inability to raise the arm or a palpable defect should not be assumed to be simple tendinitis and needs medical assessment.
Stages and Recovery Time
Stage 1: Irritable or painful phase
Pain is prominent during the movements or loads that irritate the shoulder. The priority is to reduce the most provocative activities while maintaining comfortable movement and avoiding unnecessary prolonged immobilization. The duration varies between individuals; these phases are a practical description, not a validated staging system for deltoid tendinitis.
Stage 2: Load rebuilding phase
As symptoms become more manageable, rehabilitation gradually increases shoulder movement and muscle loading. Exercise intensity should be adjusted to the response during activity and over the following day rather than progressed according to a fixed timetable.
Stage 3: Return-to-function phase
The person progressively resumes heavier work, overhead tasks or sport when movement, strength and load tolerance improve. Return should be based on function and symptom response, not simply the number of days since symptoms began.
There is no reliable, deltoid-specific recovery timeline. Recovery depends on the actual diagnosis, severity, duration of symptoms, activity demands, general health and consistency of a suitable rehabilitation plan. Worsening symptoms or little improvement despite appropriate care should prompt reassessment of the diagnosis and treatment strategy.
Clinical assessment and rehabilitation

Related background: frozen shoulder guide.
What the assessment includes
- History and load analysis: clarify onset, trauma, recent changes in sport or work, aggravating and easing activities, night pain, previous shoulder problems and the patient’s functional goals.
- Structural and functional examination: inspect for swelling, bruising or deformity; assess active and passive shoulder range of motion, resisted shoulder movements, strength and tenderness. Findings should be interpreted together because pain during resisted abduction may also occur with rotator cuff disorders.
- Differential diagnosis and referral: consider rotator cuff disease, subacromial pain, acromioclavicular or glenohumeral disorders, cervical referral, nerve involvement and fracture or tear after trauma. Imaging is not routinely needed at the first visit for uncomplicated shoulder pain, but may be appropriate when a serious lesion is suspected or symptoms fail to improve with suitable care.
Clinical assessment and rehabilitation
- Diagnosis-led plan: choose interventions according to the clinical findings, irritability, activity requirements and patient goals. Do not assume every painful deltoid region requires the same manual technique or exercise protocol.
- Exercise and manual therapy: education, temporary activity modification and progressive therapeutic exercise are central options for many shoulder tendinopathies. Manual therapy may be used as an adjunct for short-term symptom relief when appropriate; it should not replace active rehabilitation. These recommendations are extrapolated mainly from rotator cuff-related shoulder pain, not from deltoid-specific trials.
- Regular reassessment: monitor pain, range of motion, strength, sleep and relevant activities. Increase load gradually when the response is acceptable, and revise the plan if function deteriorates or progress stalls.
- Pain relief and co-management: a clinician or pharmacist can advise whether short-term analgesics or anti-inflammatory medicines are suitable, taking account of medical history and contraindications. Do not self-prescribe injections or use pain relief to repeatedly push through worsening symptoms.
- Further medical care when needed: a clinician may request imaging or refer to a physician if there is significant trauma, marked weakness, suspected tear or fracture, systemic symptoms, or persistent pain and disability despite appropriate conservative management. Injection or surgery is not a routine treatment for presumed isolated deltoid tendinitis and should only be considered after a clear diagnosis and specialist discussion.
Nutrition and Daily Tips
No specific food cures tendinitis. A balanced diet with adequate energy, protein, fruits, vegetables and fluids supports general health and recovery. Individual dietary advice may be needed for people with medical conditions. Supplements should not be assumed to heal a tendon, and high-dose products should be discussed with a qualified healthcare professional.
Temporarily reduce the movements that reliably aggravate pain, but keep the shoulder moving within a comfortable range unless a clinician advises otherwise. Follow a gradual exercise plan, avoid sudden increases in training volume, take recovery breaks during repetitive work and return to sport progressively. Stop and seek advice if exercise causes sharp pain, new weakness or a sustained worsening of symptoms.
Other Conditions and When to Get Help
Not every painful outer shoulder is deltoid tendinitis. Rotator cuff tendinopathy or tear, subacromial pain, bursitis, acromioclavicular joint disease, arthritis, cervical radiculopathy and fracture can produce similar symptoms. See a doctor or physiotherapist if you experience any of the following:
- Pain persists, worsens or repeatedly returns despite activity modification
- Pain significantly disturbs sleep or limits daily activities
- Symptoms began after a fall, collision or other significant trauma, or there is marked weakness
- There is numbness, tingling, pain extending below the elbow or new loss of movement
- The shoulder is deformed, hot or markedly swollen, or symptoms occur with fever or chest symptoms; seek urgent medical care where appropriate
Final Takeaway
Common questions
Is deltoid tendinitis the same as rotator cuff tendinopathy?
No. The deltoid and rotator cuff are different structures, although pain can be felt in a similar region. Examination helps refine the diagnosis.
Is there strong evidence for one specific treatment?
Research specific to isolated deltoid tendinopathy is limited. Broader shoulder rehabilitation principles should be applied cautiously and individually.
Should I force overhead stretches?
No. Exercise should fit the diagnosis and symptom response. Sudden weakness or loss of movement after injury should be assessed before stretching.
Assessment and rehabilitation in Dhaka
ASPC Manipulation Therapy provides physiotherapy assessment and rehabilitation in Dhaka. An appointment can help clarify your symptoms, current movement and strength, daily activity goals and whether medical referral is needed. Care should be individualized, with progress reviewed rather than a guaranteed recovery promise.
ASPC describes its assessment framework as Structural Diagnosis and Management (SDM). A named framework does not establish effectiveness for every condition. Treatment choices should follow the clinical findings, relevant guidance and the person’s preferences.
Discuss an assessment with ASPC
Related patient guides
- Frozen Shoulder: Symptoms, Causes, Recovery and Treatment
- Neck Pain: Causes, Symptoms, Exercises and Physiotherapy
Sources and further reading
Read the condition-specific guidance below alongside the assessment and exercise information in this article. Guidelines inform general care; they do not establish individual outcomes or superiority of a clinic.
- AAOS OrthoInfo patient guidance
- Rotator cuff tendinopathy clinical practice guideline; broader shoulder evidence, not a deltoid-specific trial
Editorial update: 26 October 2026. Medical information disclaimer.